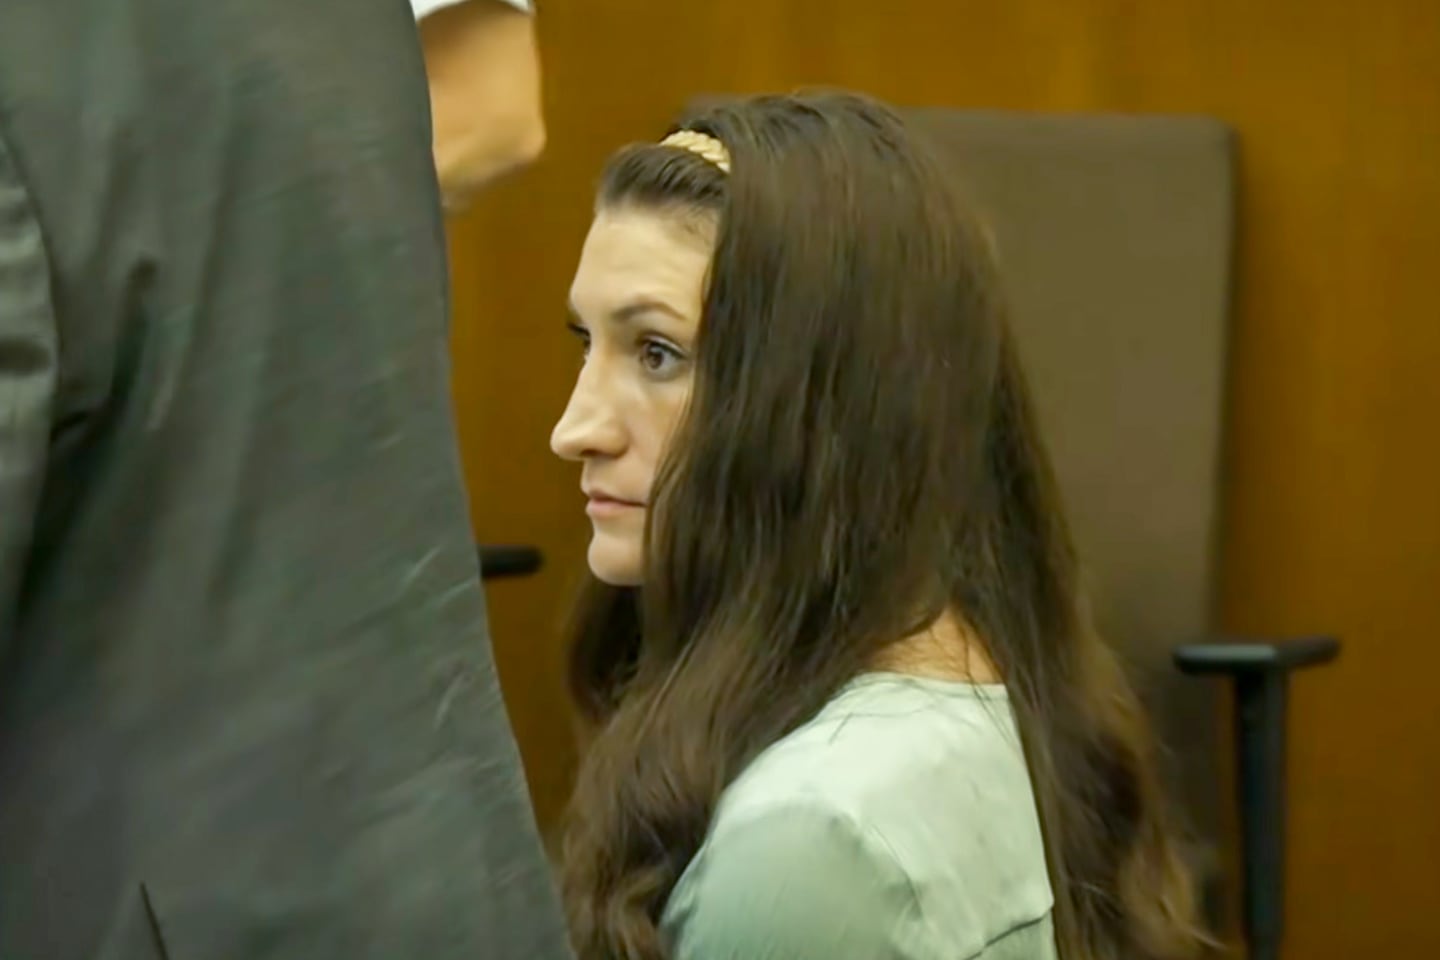The Convergence of Mens Rea and Clinical History
The second week of the Lindsay Clancy murder trial in Plymouth, Massachusetts, has transitioned from procedural preliminaries to a rigorous examination of the defendant’s mental state at the time of the offense. Central to the litigation is the conflict between the prosecution’s narrative of premeditated intent and the defense’s assertion of a lack of criminal responsibility due to postpartum psychosis. Clancy’s presence—conveyed via wheelchair and emotional volatility—provides a visceral backdrop to the technical legal debate over her cognitive capacity on January 24, 2023.
Clinical Baselines vs. Acute Psychotic Breaks
Testimony from Dr. Alia Goodheart, a psychiatrist who treated Clancy during an inpatient stay weeks before the incident, has emerged as a pivotal evidentiary hurdle for the defense. Dr. Goodheart testified that Clancy exhibited no clinical signs of psychosis during her evaluation, identifying her family as a protective factor against self-harm. This assessment establishes a baseline of perceived stability, which the prosecution leverages to argue that the subsequent tragedy was not a product of involuntary delusion, but a calculated sequence of actions.
By highlighting this lack of documented psychosis in a controlled environment, the Commonwealth shifts the burden of proof to the defense, requiring them to demonstrate a rapid and total psychological collapse following discharge. The prosecution argues that Clancy’s behavior—utilizing exercise bands with precision—demonstrates a level of focus and physical coordination inconsistent with the disorganized thinking typical of a psychotic break.
The Evidentiary Weight of Contemporaneous Records
Clancy’s personal diaries have been repositioned from mere domestic accounts to critical diagnostic tools. For the defense, these entries serve as a roadmap of a mind deteriorating under the weight of postpartum depression, providing the ‘moral and mental’ framework for an insanity plea. Conversely, the prosecution interprets the granular detail of these writings as proof of a high-functioning, organized mind capable of complex planning. This strategic use of the same evidence illustrates the trial’s central tension: whether the defendant’s struggles should be humanized as a medical tragedy or pathologized as a precursor to criminal intent.
Legal Standards and Institutional Scrutiny
Under Massachusetts law, the defense must prove that Clancy lacked the ‘substantial capacity’ to appreciate the wrongfulness of her conduct or to conform her behavior to the law. This high threshold necessitates a synthesis of psychiatric history and immediate behavioral patterns. The trial also invites scrutiny of the medical institutions involved; the fact that Clancy was cleared for discharge shortly before the event raises systemic questions regarding the efficacy of psychiatric risk assessments for postpartum patients.
Procedural Friction and Courtroom Decorum
The trial has also faced procedural turbulence, most notably a ‘hot-mic’ incident where defense counsel Kevin Reddington alleged a prosecutor made a disparaging remark during Clancy’s emotional breakdown. While the District Attorney’s office clarified the comment was a technical instruction regarding autopsy photos, the incident underscores the heightened emotional stakes. These moments of friction, though secondary to the evidence, influence jury perception regarding the professional conduct and empathy of both legal teams as they navigate a case of profound domestic tragedy.