
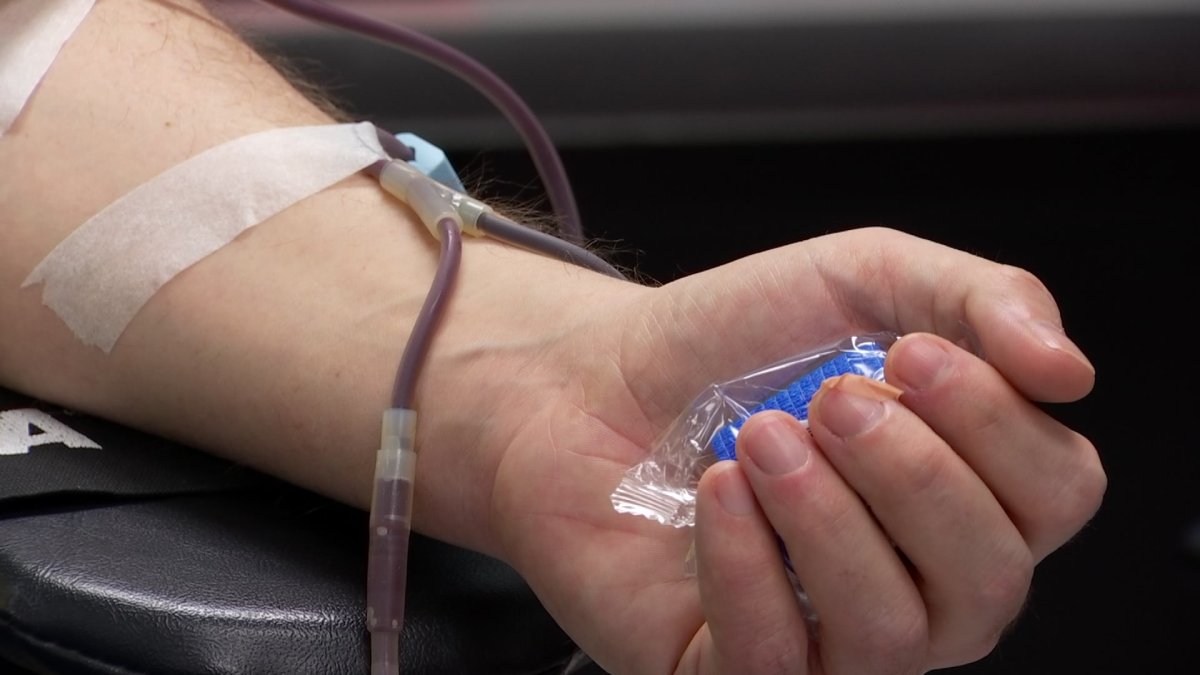
The national blood supply infrastructure currently navigates a complex operational landscape, characterized by both proactive resilience strategies and acute systemic vulnerabilities. While collaborative networks demonstrate effective disaster response capabilities, broader supply chain pressures are simultaneously triggering emergency declarations and strategic shifts in donor engagement across the sector.
Houchin Community Blood Bank’s five-year partnership with the Blood Emergency Readiness Corps (BERC) exemplifies a strategic approach to mitigating localized supply disruptions. This collaboration establishes a distributed network designed to ensure critical blood resources are available for mass casualty events and natural disasters, thereby enhancing regional healthcare system stability.
BERC, initiated in 2021 with seven founding centers, has expanded into a nationwide consortium encompassing 38 blood centers across nearly every state. This growth reflects a sector-wide recognition of the imperative for coordinated, rapid-response mechanisms to address unpredictable, high-demand scenarios that can overwhelm individual blood bank capacities.
The operational efficacy of BERC is evidenced by its 18 activations since inception, facilitating the deployment of over 1,600 units of blood to affected regions. This pooled resource model minimizes the risk of single-point-of-failure scenarios, transforming localized crises into manageable events through collective action and pre-established logistical pathways.
For member organizations like Houchin, participation in BERC provides a critical layer of operational security. The assurance of having 37 partner centers ready to supply blood in the event of a disaster impacting Kern County significantly de-risks local emergency preparedness, allowing for more robust community response planning.
This collaborative framework underscores a strategic pivot within the blood banking industry towards mutual aid and shared responsibility for national health security. It represents an institutional investment in distributed resilience, moving beyond isolated stockpiling to an integrated, responsive supply chain capable of dynamic resource allocation.
Concurrently, the broader national blood supply faces an acute and escalating crisis, as highlighted by emergency declarations from the American Red Cross and Carter BloodCare. These pronouncements signal a significant operational challenge, compelling hospitals to confront difficult decisions regarding patient care prioritization.
The Red Cross’s declaration of a national blood shortage emergency, only the second such instance in its history, underscores the severity and systemic nature of the current deficit. This historical context indicates that the present conditions extend beyond typical seasonal fluctuations, pointing to deeper structural pressures on the supply chain.
A 25% drop in blood supplies during June precipitated this emergency, reflecting a confluence of factors that strain the voluntary donation model. Such sharp declines necessitate immediate and drastic operational adjustments across the entire healthcare continuum, impacting both emergency and elective medical procedures.
The limited availability of blood products forces medical facilities to reserve existing supplies for life-or-death situations. This triage protocol inevitably leads to delays for patients awaiting scheduled procedures, creating significant operational bottlenecks and ethical dilemmas for medical professionals who must prioritize urgent needs.
O-negative blood, universally compatible and critical for trauma cases, is in particularly urgent demand. Its scarcity disproportionately impacts emergency services, where immediate transfusion is often life-saving, highlighting a specific vulnerability within the overall blood inventory management system.
Seasonal patterns historically contribute to lower donation rates during summer months, a trend exacerbated this year by extreme heat and major cultural events like the World Cup. These external factors introduce unpredictable variables into an already delicate supply-demand equilibrium, complicating donor recruitment efforts.
The confluence of these environmental and social factors reveals the inherent fragility of a blood supply system heavily reliant on consistent public engagement and voluntary contributions. It places significant operational strain on blood collection agencies, requiring intensified outreach and resource mobilization.
In response to these critically low levels, Carter BloodCare has initiated a policy of paying for donations, representing a significant strategic shift within the non-profit blood banking sector. This move reconfigures the traditional altruistic model of blood acquisition, introducing a transactional component to incentivize participation.
The decision to offer financial compensation for donations carries substantial operational and ethical implications. It could potentially broaden the donor pool by attracting individuals motivated by economic incentives, but it also raises questions about the long-term sustainability and public perception of blood donation as a civic duty.
From a competitive standpoint, this payment model could create new dynamics among blood collection organizations. Agencies that maintain a purely voluntary donation model might face increased pressure to compete for donors, potentially leading to broader industry-wide shifts in recruitment strategies and cost structures.
The financial implications for Carter BloodCare involve a direct increase in operational expenses associated with donor acquisition. This strategic investment reflects the acute severity of the shortage, prioritizing immediate supply replenishment over traditional cost-containment measures in a crisis.
This shift also necessitates rigorous regulatory and quality control considerations to ensure the integrity and safety of the blood supply. Introducing financial incentives requires careful management to prevent any unintended consequences that could compromise donor screening or product quality standards.
The contrasting narratives of BERC’s collaborative success and the national shortage underscore the dual challenge facing the blood supply sector: building robust, distributed resilience for specific, high-impact events, while simultaneously managing the persistent, systemic pressures on daily inventory levels.
This dynamic has brought the entire blood supply ecosystem to a critical re-evaluation point, signaled by the Red Cross’s historical emergency declaration and Carter BloodCare’s strategic pivot to paid donations. These events highlight an urgent need for comprehensive strategies that address both episodic crises and chronic supply-demand imbalances.
The operational strain on hospitals, manifested through delayed procedures and resource prioritization, creates downstream effects on patient outcomes, healthcare system efficiency, and public trust. Transparent communication and proactive solutions are essential to mitigate these impacts.
Balancing the demonstrated benefits of collaborative networks like BERC with the foundational necessity of sustainable, everyday donor recruitment is a core strategic imperative. The current crisis starkly reveals that while disaster preparedness is advancing, the basic blood supply remains vulnerable to a complex interplay of environmental, social, and economic factors.
Long-term financial stability for blood banks faces potential disruption from increasing reliance on paid donations, which could alter non-profit operational models and lead to higher blood product costs borne by healthcare providers and, ultimately, patients or insurance systems.
Public health policymakers are under renewed pressure to assess existing frameworks for blood collection, distribution, and emergency response. This situation may catalyze discussions on national stockpiling, diversified donor recruitment campaigns, and potential regulatory reforms to fortify the supply chain.
The media’s critical role in amplifying these alarms is dual-edged, vital for public mobilization but also for shaping perception of the blood supply’s reliability. Accurate, urgent, and confidence-building communication is paramount to drive donor action without undue panic.
Ultimately, the documented facts position the blood banking sector at a strategic inflection point. The imperative for sustained, diverse donor engagement – whether through altruistic appeals or new incentive structures – remains paramount. Future resilience will hinge on a multi-faceted approach integrating technological advancements, community outreach, robust inter-organizational cooperation, and adaptive policy, collectively shaping the responsiveness of the entire healthcare system.
Photo by geraldoswald62 on Pixabay.