
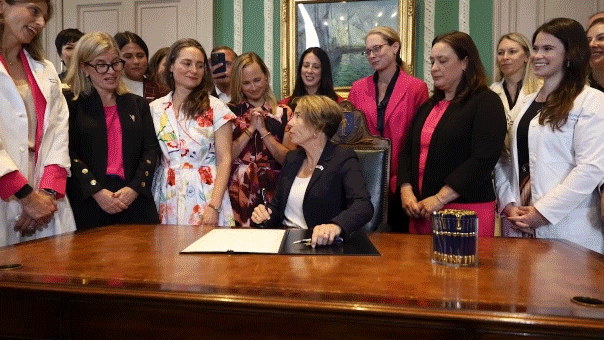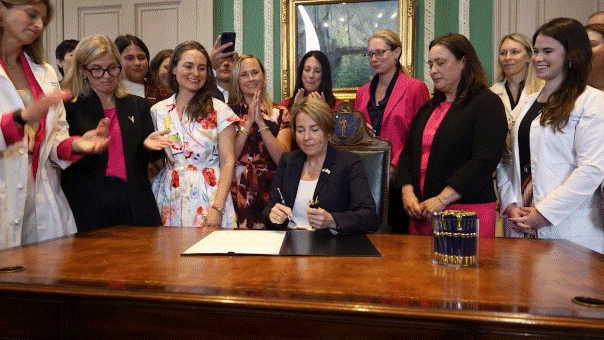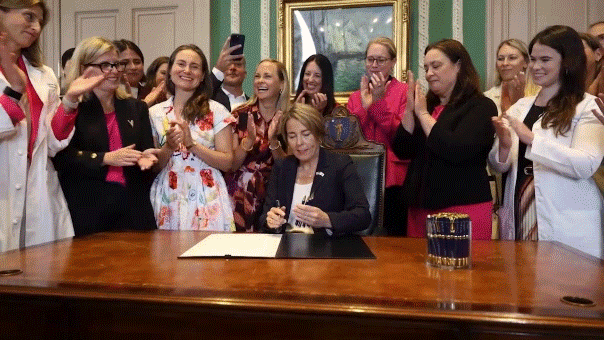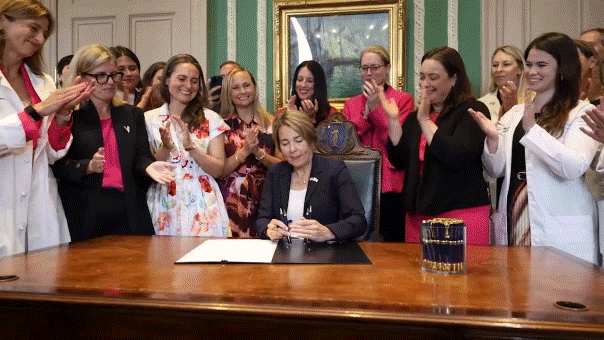
The enactment of the Prioritizing Patient Access to Care Act by Governor Maura Healey represents a structural pivot in Massachusetts’ healthcare regulatory architecture. By dismantling the previous 24-week gestational threshold, the Commonwealth has transitioned from a rigid statutory framework—predicated on specific medical exceptions—to a model defined by clinical professional judgment. This legislative realignment makes Massachusetts the 11th state to eliminate fixed gestational boundaries, effectively internalizing high-acuity reproductive care within its borders.
From Statutory Constraints to Clinical Autonomy
Previously, Massachusetts law restricted post-24-week procedures to specific exigencies: the preservation of patient life or health, or lethal fetal anomalies. The new mandate replaces these legal benchmarks with a broader standard centered on the “professional judgment of a physician.” This shift fundamentally alters the risk landscape for providers; by removing the state as an intermediary in late-term medical scenarios, the law reduces the administrative friction typically exerted by hospital ethics boards and legal departments attempting to interpret static statutes.
Furthermore, the removal of legal penalties for clinicians serves as a strategic intervention to stabilize the state’s medical workforce. In a national environment where legal exposure drives provider flight, this immunity acts as an institutional barrier, ensuring that specialized personnel can exercise the full scope of their expertise without the threat of professional sanction or litigation.
Mitigating Medical Migration and Economic Externalities
A primary driver for this reform was the systemic failure of the previous regime, which forced residents to seek care in distant jurisdictions. This “medical migration” imposed significant financial and psychological costs on families, often reaching thousands of dollars in travel and out-of-network fees. By internalizing these services, Massachusetts captures the economic activity associated with high-acuity care while streamlining the care pathway for high-risk pregnancies.
From a systemic perspective, localizing this care enhances continuity and integrates support systems that were previously fragmented by interstate travel. The legislation effectively addresses a leakage of healthcare capital, ensuring that the state’s advanced medical infrastructure serves its population during acute crises rather than delegating responsibility to external health systems.
Strategic Political Capital and Future Regulatory Risks
The timing of the bill’s signing—during the final hours of the legislative session—highlights its utility as a tool of political differentiation. Governor Healey has positioned Massachusetts as a “haven” for reproductive access, leveraging state autonomy to contrast with restrictive national trends. This strategic posturing reinforces the state’s identity as a leader in healthcare liberalization, yet it also invites scrutiny from national advocacy groups, such as SBA Pro-Life America, potentially exposing the state to external legal challenges.
While the law provides immediate clarity, the long-term interpretation of “professional judgment” remains a dynamic variable. The state has essentially delegated its oversight role to professional bodies, assuming that clinical ethics and peer-review processes will provide sufficient guardrails. The success of this model will depend on the continued alignment of political leadership and medical expertise in an increasingly polarized national environment.
Conclusion: A New Era of Expertise-Driven Regulation
The Prioritizing Patient Access to Care Act marks the conclusion of an era defined by rigid timelines and the commencement of a framework defined by medical nuance. By prioritizing clinical autonomy over legislative mandates, Massachusetts has established a regulatory blueprint that emphasizes the patient-provider relationship. As this framework is operationalized, the focus will shift to monitoring health outcomes and the state’s ability to defend its legislative sovereignty against national political pressures.
